


Page History
...
| Info | ||
|---|---|---|
Follow the instructions below to complete each form based on your Open Enrollment changes. If you’re adding yourself or dependents, have their date of birth and Social Security number ready. SignNow securely limits access to your information to you and the HR team only. For questions, contact benefits@reliant.org. Form links:
|
SignNow
| UI Expand | |||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| |||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||
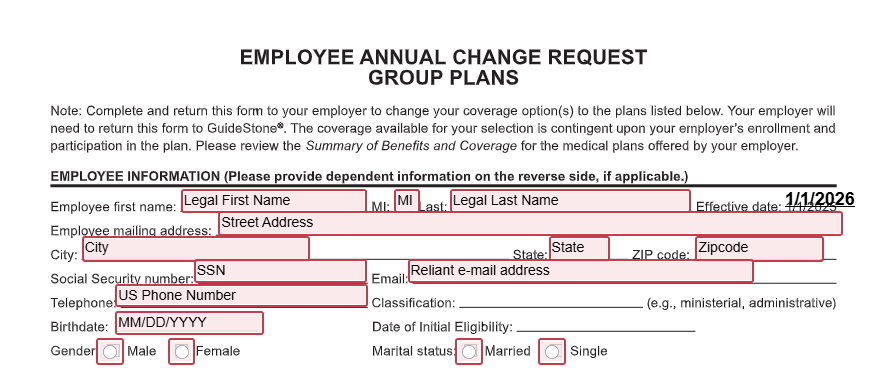
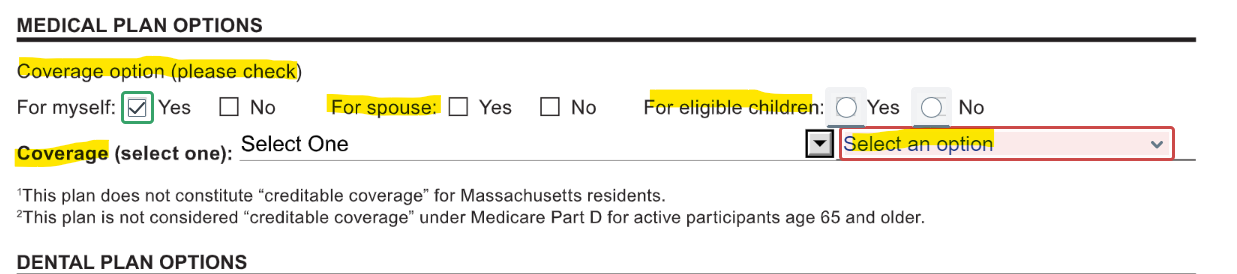
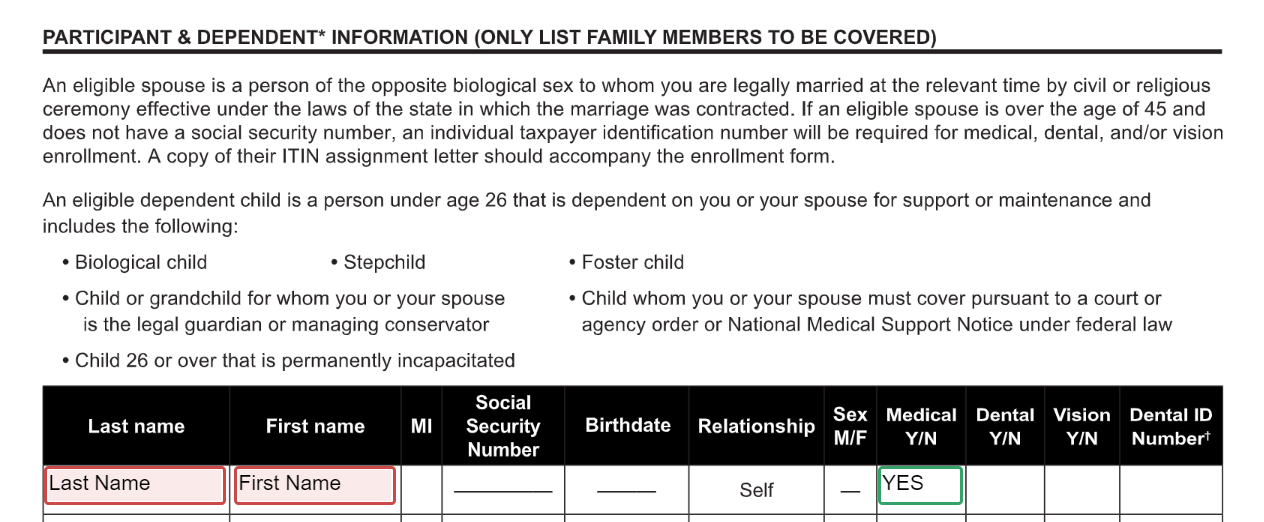
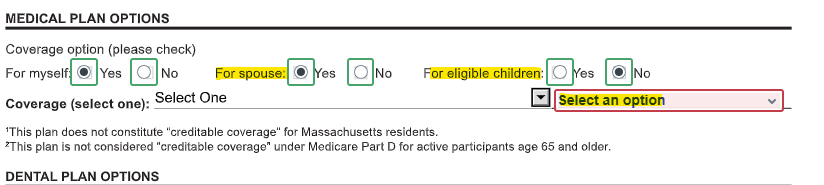
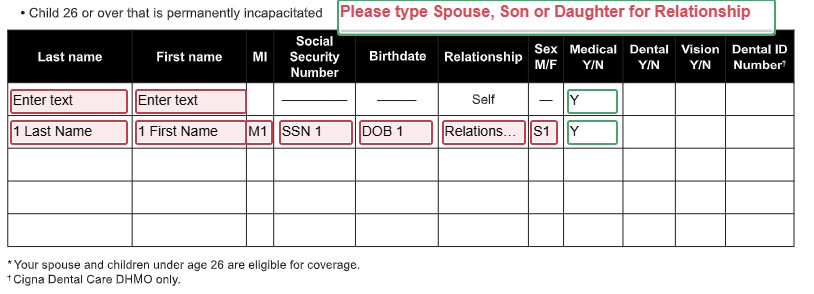
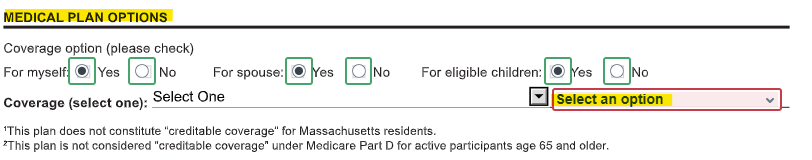
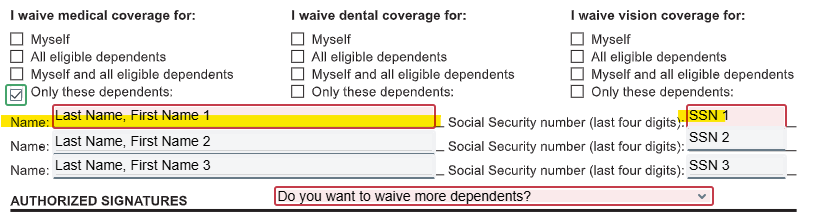
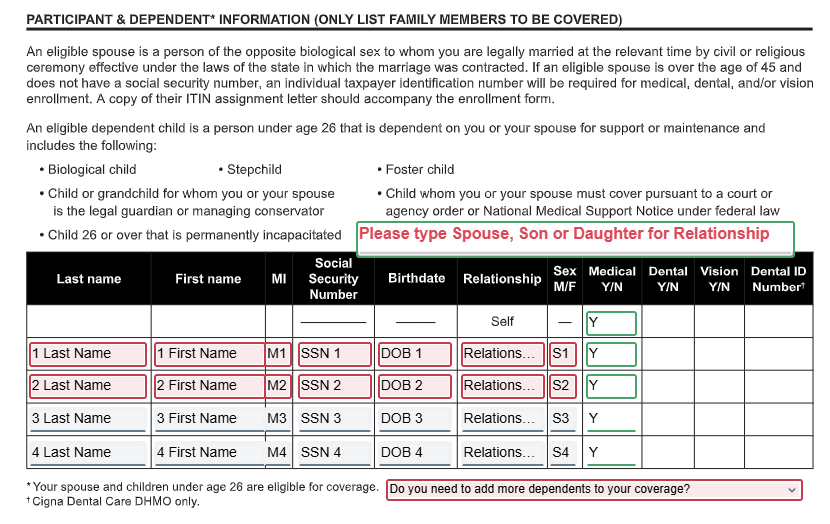
If you don’t currently have medical insurance through Reliant but would like to enroll, please complete this form. To help you fill it out, we’ve included a few common scenarios below based on who you’re enrolling. Click the one that applies to you to get step-by-step guidance
|



| UI Expand | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| ||||||||||||
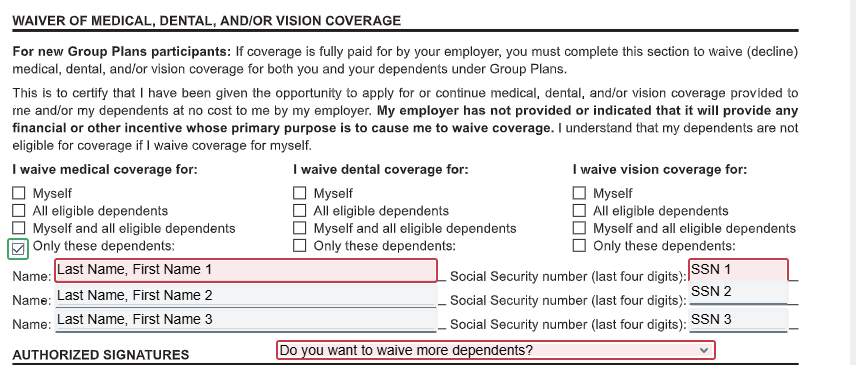
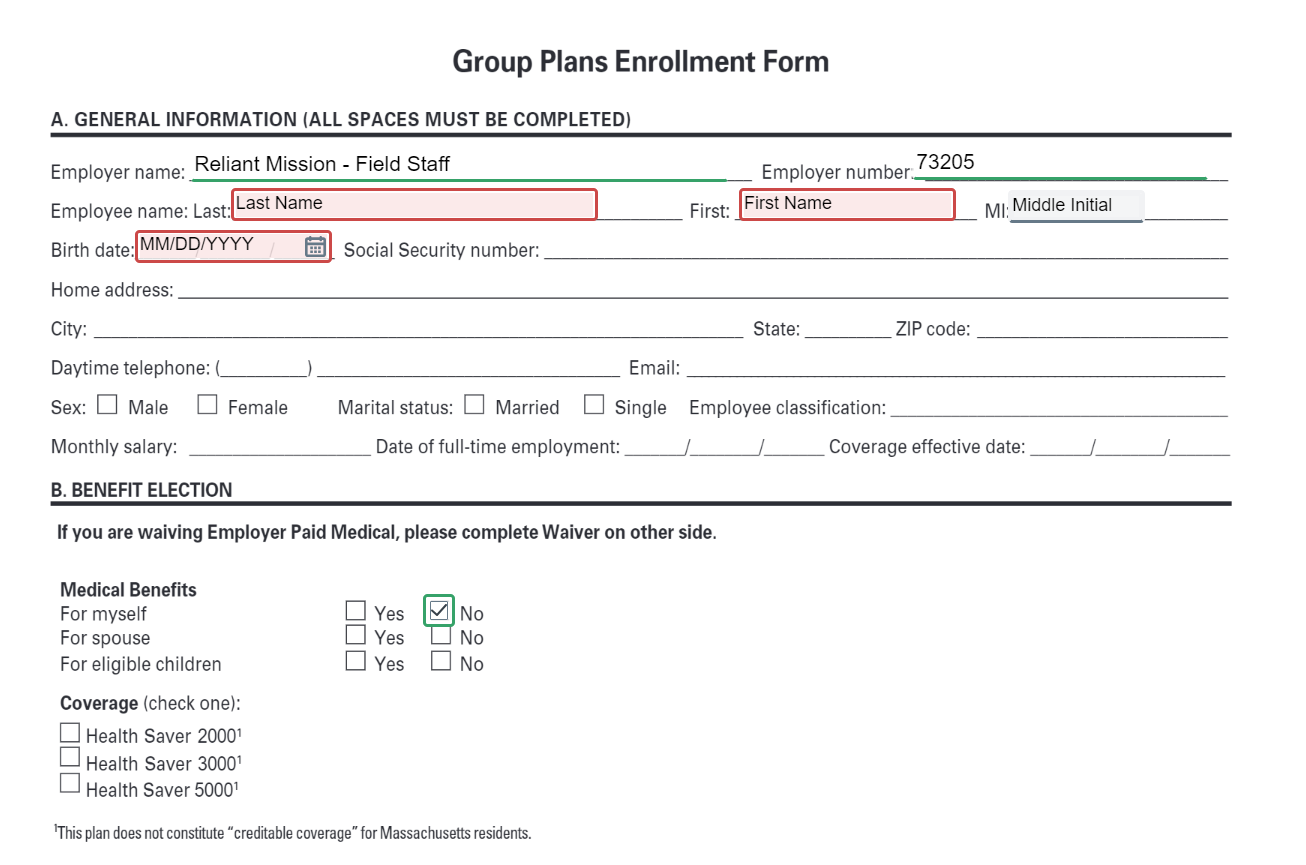
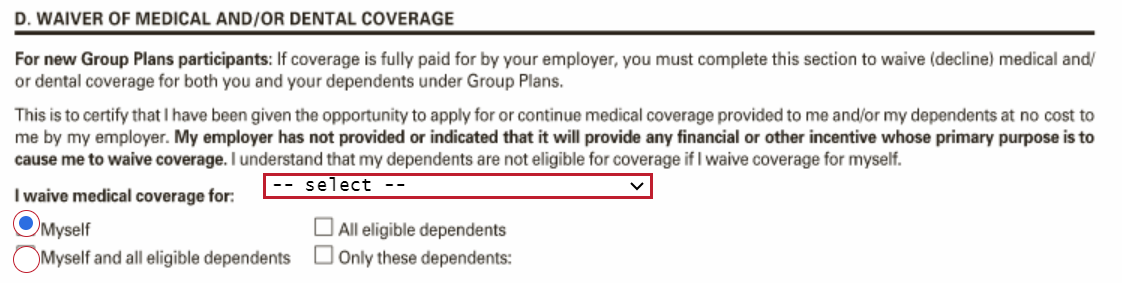
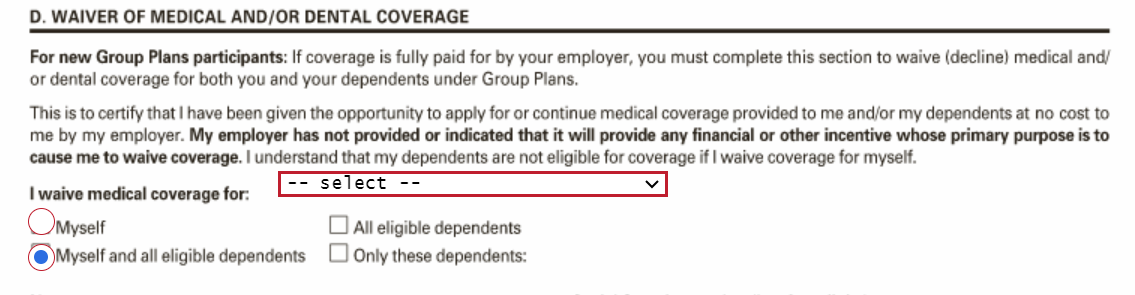
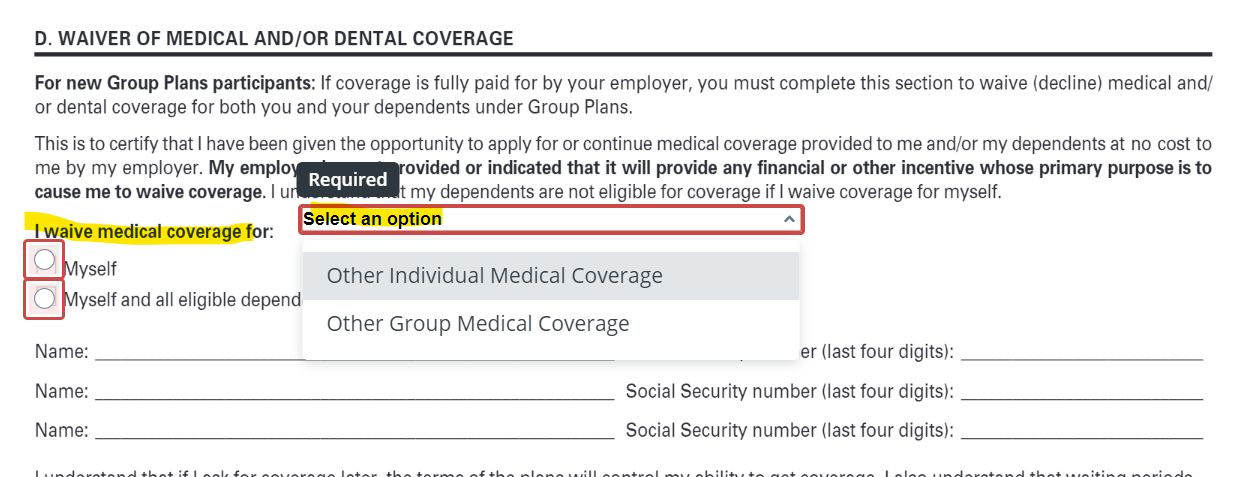
If you are terminating all your medical coverage for yourself and dependent(s) (a dependent is anyone else who is covered on their insurance plan, this includes their spouse), please complete this form via the instructions below. Demographic Info Required:
|

| UI Expand | ||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| ||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||||
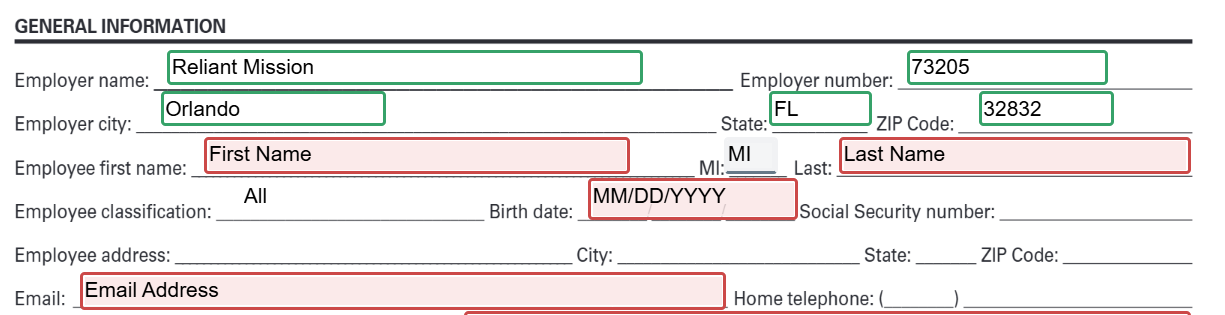
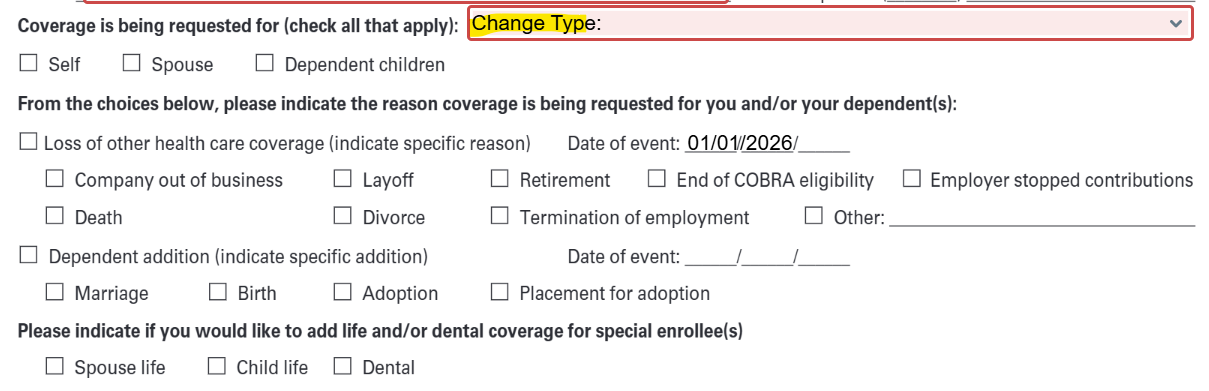
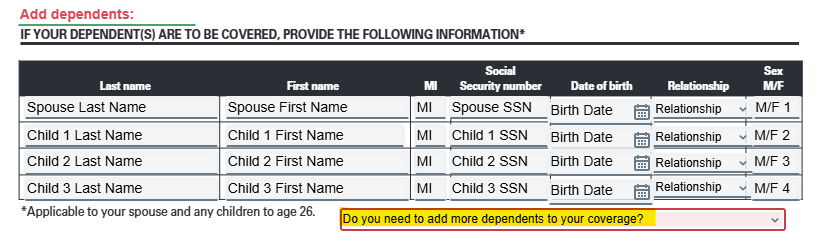
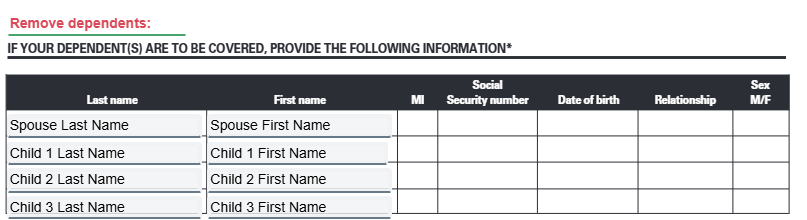
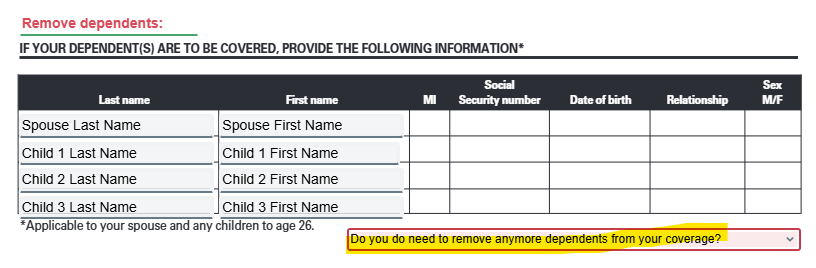
If you would like to make changes to your current medical plan, this is the form to complete. Please note the demographic information that may be required on this form depending on the change you are making. Demographic Info Required:
|
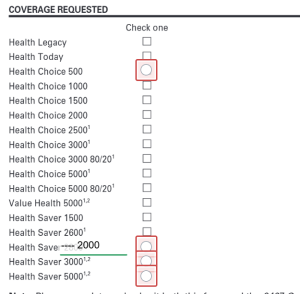


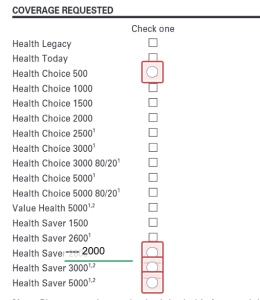


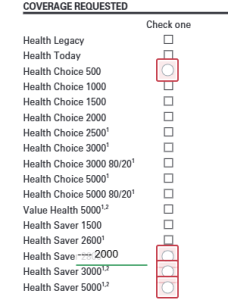
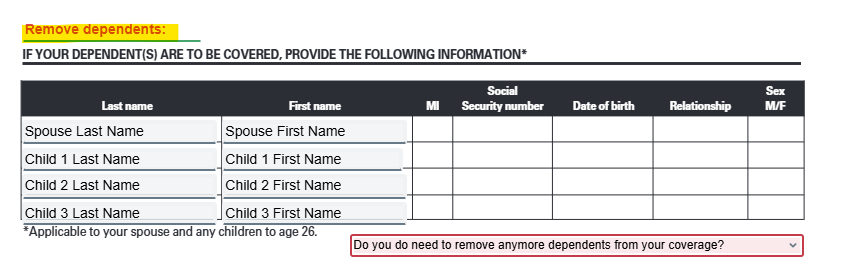


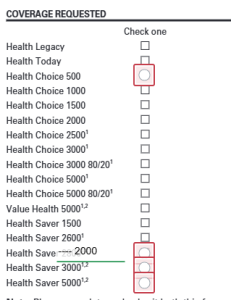
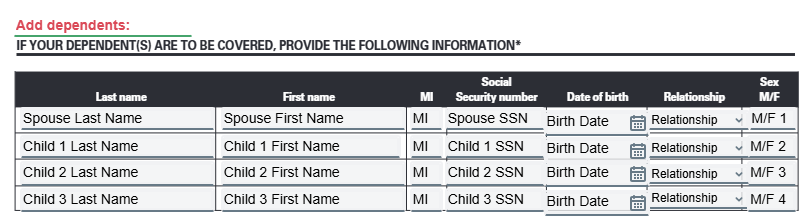
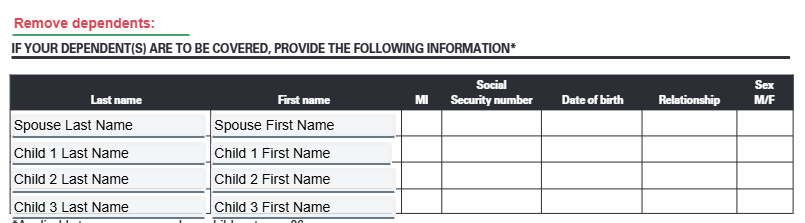
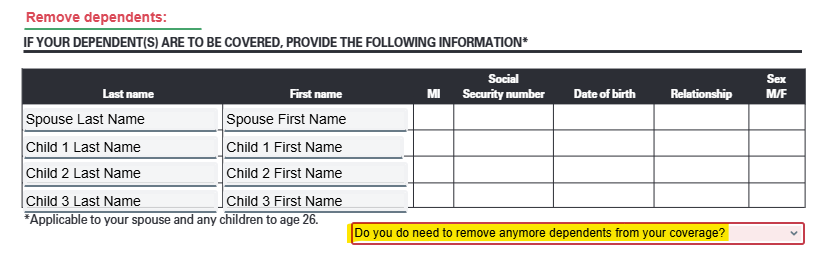


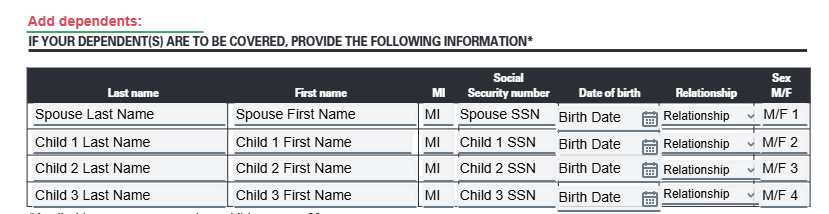



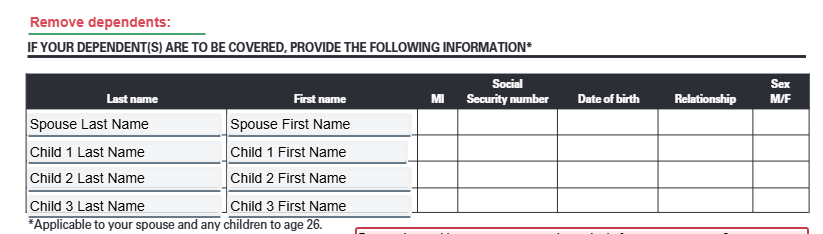
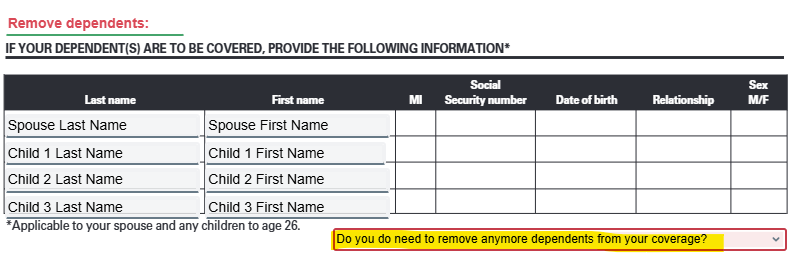


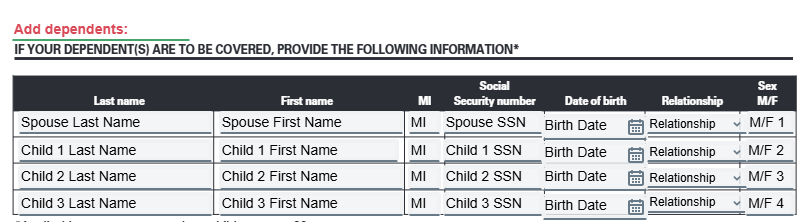

...
| UI Expand | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| ||||||||||||
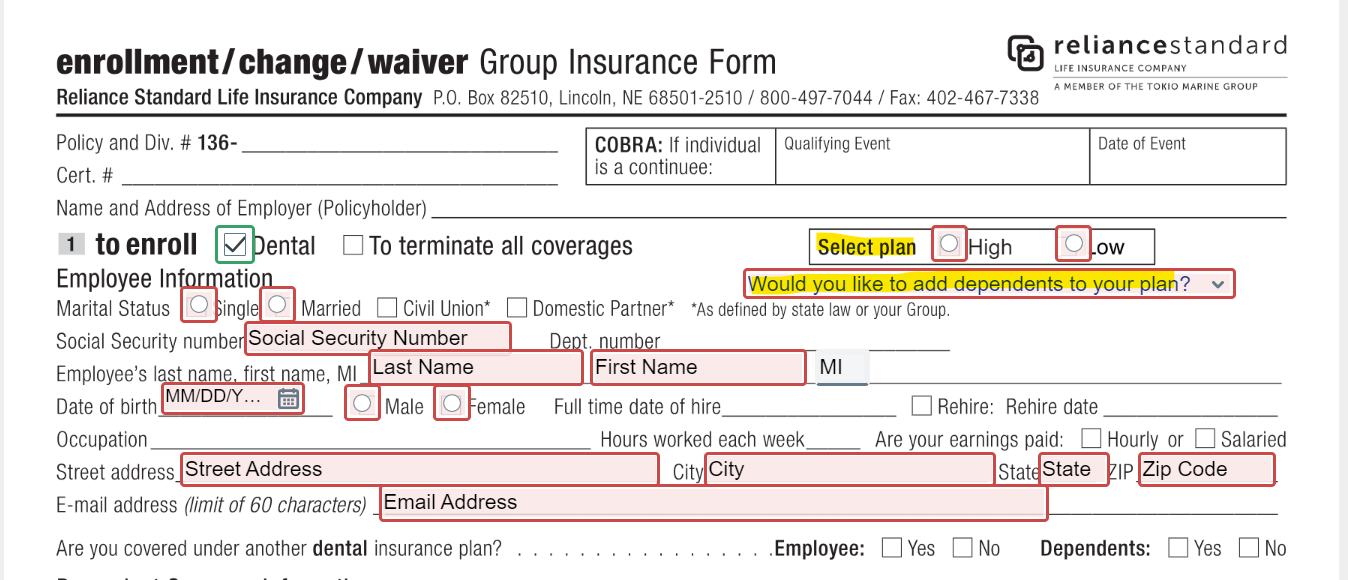
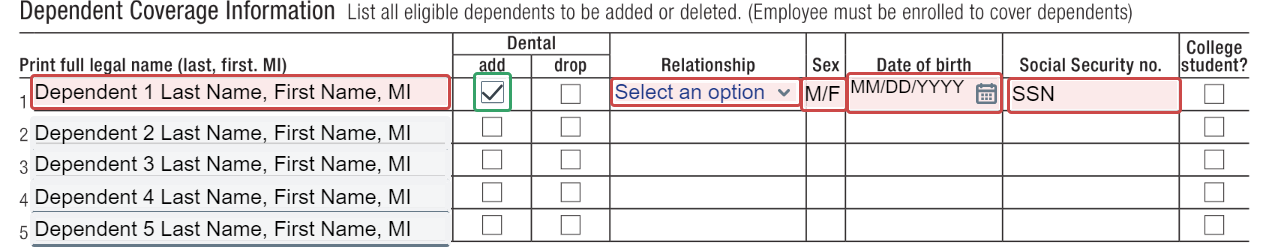
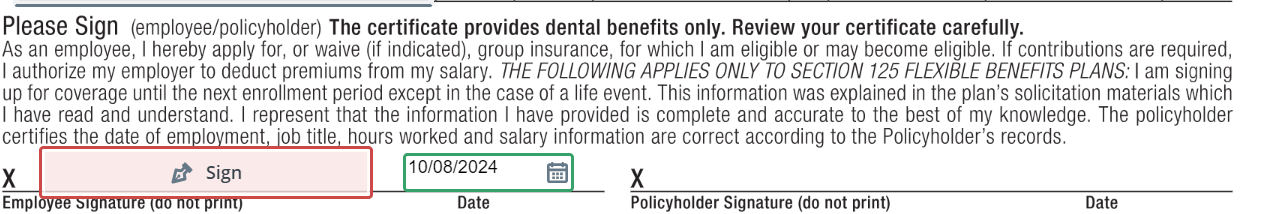
If the Field employee does not currently have dental insurance through Reliant but would like to enroll, please have them complete this form via the instructions below and their coverage will go into effect on January 1st, 2026 Demographic Info Required:
|

| UI Expand | ||||||||
|---|---|---|---|---|---|---|---|---|
| ||||||||
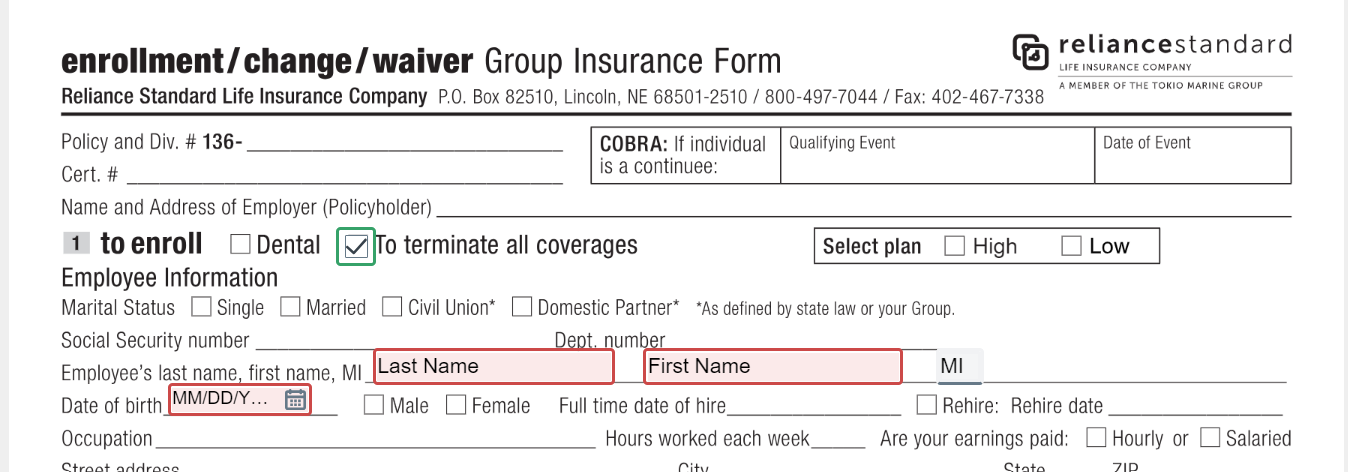
If the Field Employee is terminating all dental coverage for them and their dependent(s), please have them complete this form via the instructions below. Demographic Info Required:
|


| UI Expand | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|
| ||||||||||
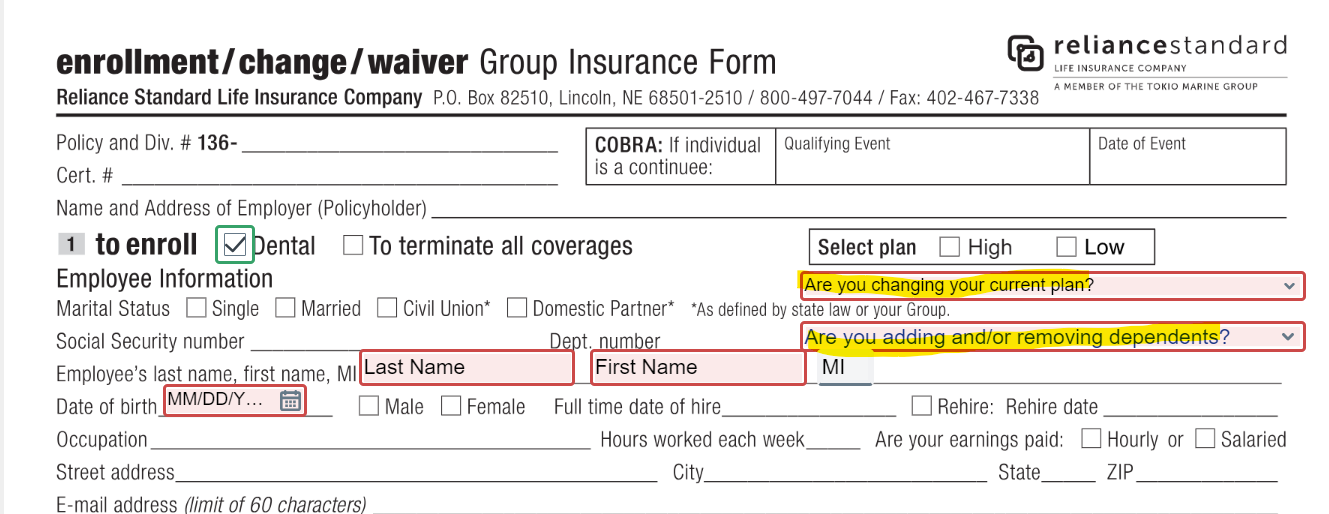
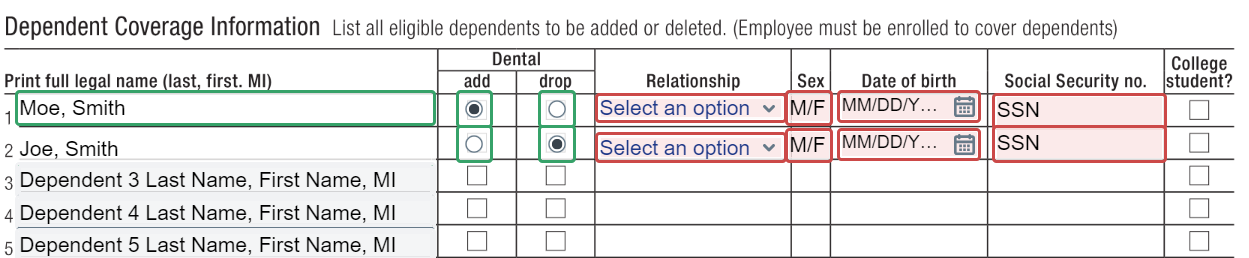
If the Field Employee is currently enrolled in dental insurance but would like to add dependent(s) (individuals covered on their plan), terminate coverage for their dependent(s), or change coverage levels, they will use the Change Forms and complete it with the changes they would like to make. Note, this change will go into effect on January, 1st 2026. Demographic Info Required:
|


Microsoft Forms
| UI Expand | ||
|---|---|---|
| ||
This is a Microsoft secured form and it is used to make the following elections for 2026:
|
...
